






Pearl is a clinical professor of plastic surgery at the Stanford University School of Medicine and is on the faculty of the Stanford Graduate School of Business. He is a former CEO of The Permanente Medical Group.
During my residency at Stanford, I traveled to Mexico with a group of surgeons to operate on children with cleft lips and palates. On the first day, I watched in awe as the team leader meticulously realigned the tissues of the lip, mouth and nose of a 3-month-old boy, leaving behind nothing but a faint scar — all in just 90 minutes.
I immediately fell in love with plastic and reconstructive surgery. As a surgeon, I visited over a dozen countries to repair the cleft lips and palates of children. But later, in my leadership role as CEO at Kaiser Permanente, extended travel proved impossible. And I missed those trips dearly.
Last month marked my first global surgery mission in many years. Not only did our time in the Philippines reignite my passion for global surgery, but it also left me with three surprising lessons for American health care:
Without mission and purpose, medicine proves exhausting
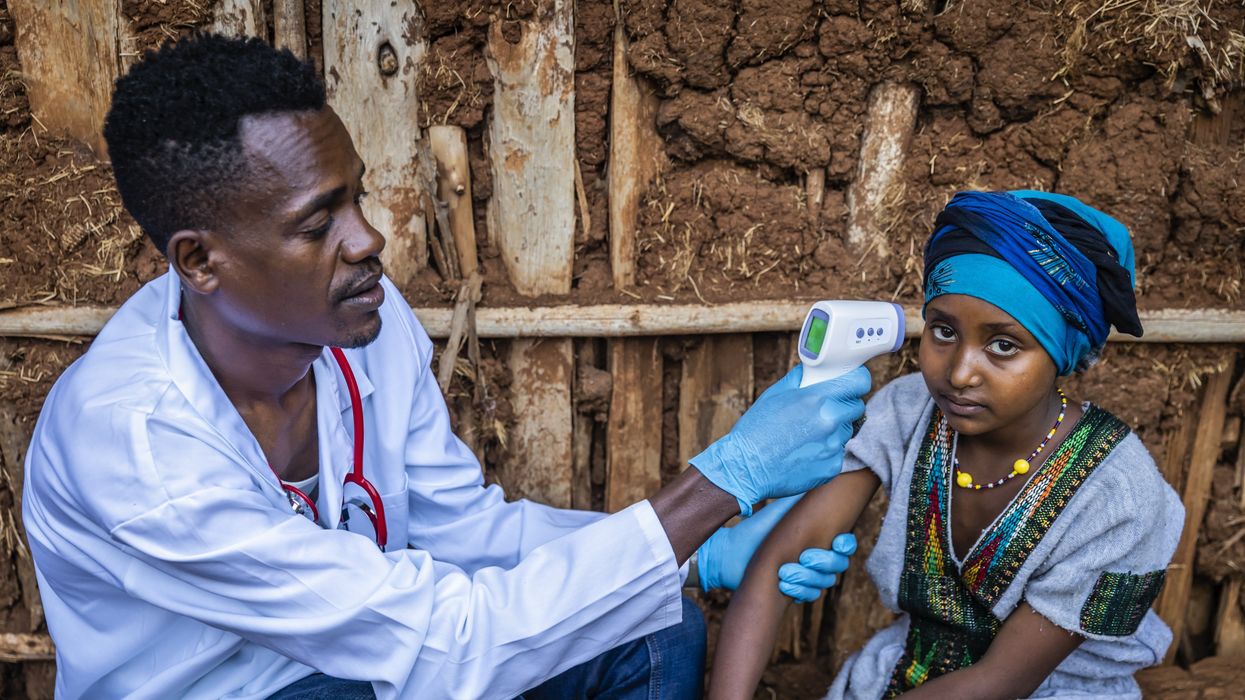
Surgical trips are physically and emotionally demanding. Far from the sterilized corridors of American hospitals, you are plunged into environments where resources are scarce and the needs overwhelming. In remote towns and underdeveloped cities, you operate in tight spaces with erratic electricity and limited clean water. The days stretch long, with five to seven surgeries in a 12-hour day.
Each child you treat carries a story of hardship and hope, their families’ eyes filled with a mix of fear and optimism. And just as you start to tire from the heat and yearn for a good night’s sleep, another mother arrives. She has walked for two days through the mountains with a child in her arms, praying her baby can be added to the surgical schedule. There is no saying “no” to this. You immediately become reinvigorated.
After a physically trying week, you return to the United States not exhausted, but emotionally replenished. Nearly every clinician who has participated in a surgical mission feels the exact same way.
American health care today obscures the fundamental mission and purpose that motivates clinicians. Physicians find themselves ensnared in a web of administrative tasks and insurance disputes. For many doctors, this noble calling has become just a job.
To revive the profession and address the burnout crisis that affects more than 60 percent of clinicians, a renaissance of purpose is imperative.
To get there, we must pivot away from the transactional “fee for service” financial model that rewards doctors for the sheer quantity of services rendered. In its place: a reimbursement model led by clinicians who are paid based on the quality of clinical outcomes achieved.
Inherent in the privilege of healing is the duty to lead this transformation. Taking on that accountability — and thereby eliminating the care restrictions that insurance companies impose — will rejuvenate, not further fatigue, health care professionals.
American doctors are excellent but so are physicians around the globe
U.S. physicians believe that training outside the States is a second-rate education. It’s time to alter that perspective.
During my week in the Philippines, I had the pleasure to work alongside five local physicians, often at adjoining operating room tables. They’d trained in residency and fellowship programs all around the world to maximize their expertise. To a person, their results matched the leading pediatric hospitals in the United States.
Although American doctors have access to the best facilities, machines and materials, physicians in other nations have a competitive advantage that comes from higher volume. The best way to hone any medical skill is through repetition and experience. American surgeons lag their global colleagues in this area.
U.S. clinicians bring a wealth of knowledge that can greatly benefit doctors worldwide, yet there are equally rich lessons to learn from the experiences and practices of physicians abroad.
In the U.S. today, doctors adhere to minimum surgical volume standards. Patient outcomes would improve tremendously if, instead, our nation set benchmarks for superior performance. Combining high-volume surgical experience with our advanced technologies and top-notch facilities would produce superlative clinical outcomes.
But first, America’s health care professionals need to embrace humility and be open to learning from our global colleagues.
U.S. resources are vast but access is still scarce
In countries like the Philippines, health care challenges are magnified by economic constraints. Despite government coverage, per capita health care spending remains low, under $200 annually. This financial reality forces difficult choices, leaving significant gaps between the health care needs of the population and the services available.
Witnessing these disparities firsthand is a poignant reminder of the abundance the United States enjoys, with health care spending now exceeding $13,000 per American. And yet, despite our nation’s wealth, independent studies reveal that U.S. health care ranks last among a dozen wealthy nations and near the bottom of 38 OECD countries in more than a dozen health measures.
The United States has earned its distinction as home to the most expensive and least effective health care system in the developed world. This isn’t just because of our 30 million uninsured citizens (and tens of millions who are underinsured). It’s the result of decades of underinvestment in primary care, tolerance of inefficient hospital systems and exorbitant drug prices.
The challenge of transforming American health care is daunting, and it requires a willingness to embrace change and confront uncomfortable truths. Observing the efficiency and ingenuity of less affluent nations inspires a reevaluation of our own care-delivery practices and health care finances.
The biggest problem in our health care system isn’t a lack of money. It’s the deficit in leadership and innovation.
Volunteering on global missions offers invaluable perspectives that could catalyze change in the United States. I’m optimistic that by learning from countries that achieve remarkable outcomes with modest means, we can enhance clinical outcomes, reduce clinician burnout, and make quality health care accessible and affordable for all Americans.












U.S. President Donald Trump speaks during a“ Steel Across America” event ahead of the 25th anniversary of the Sept. 11th attacks on the Ellipse near the White House on Sept. 8, 2026 in Washington, D.C. President Trump welcomed 9/ 11 first responders to the Tunnel to Towers Foundation’ s“ Steel Across America” event featuring a 16,900- pound, 21- foot steel beam recovered.
For Trump, even 9/11 is an opportunity
There was a reason organizers of the 9/11 ceremony in Manhattan told President Trump he could not speak at this year’s memorial service.
A good one, it turns out.
Because in a speech he gave on Tuesday in Washington, he did exactly what they were presumably worried about — he made it about himself.
According to The New York Times, Trump had wanted a speaking role at the service, but the National Sept. 11 Memorial and Museum, which oversees the site, said no, as they’ve maintained for the past decade-plus that the venue and event should be nonpartisan.
Trump has long used awful tragedies to either puff himself up, trash political opponents, or sell lies to the American people.
He blamed a deadly plane crash at Washington National Airport last year on diversity, equity and inclusion policies. He blamed Puerto Ricans for the devastation they endured after Hurricane Maria in 2017. He reportedly considered withholding disaster relief after the California wildfires based on the way affected regions voted. In an interview on Fox News meant to commemorate the 75th anniversary of D-Day in Normandy, he used the occasion to slam former House Speaker Nancy Pelosi…with graves of the dead behind him.
And now, as we approach the 25th anniversary of what many New Yorkers consider the darkest day in modern history, Trump has done it again.
He told a rambling, nonsensical story — one he’s told before — about going to Ground Zero just after terrorists flew two commercial jets into the twin towers. In the story, which no one has been able to verify, despite multiple attempts, he says firefighters had to carry him out of One Liberty Plaza, also known as the U.S. Steel Building, because they thought it was about to collapse.
As CNN fact checker Daniel Dale notes, there’s no evidence Trump went into this building, especially at a time when NYPD and NYFD had locked down the area. There’s no evidence that building was collapsing — in fact, it was deemed structurally sound and reopened within two months of the attacks. There’s no evidence he was carried out of it by firefighters.
But the lie isn’t even the worst part. Pretend it was all true — why would the leader of our country, and a New Yorker, decide to make that tragic day about himself?
Because that’s who Donald Trump is. He’s a malignant narcissist.
He’s also, incidentally, a terrible and ineffectual president, who’s made ill-fated decisions that he has to keep defending, and there’s nothing he won’t do to make himself look and feel better.
Within the first two minutes of his speech, he was cravenly using 9/11 to justify and promote his dumb war in Iran — two events separated by 25 years and 6,000 miles.
“And I will tell you, we’re right now fighting because we have a certain nation that wanted a nuclear weapon, they were very close to getting it, and now they have no chance at getting it. They will never have a nuclear weapon. Iran will not have a nuclear weapon. And they’ve been punished greatly. As you know, we’ve really taken it to them.”
As a New Yorker who lived through 9/11, still one of the worst days of my life, I’m utterly sickened by Trump’s crass, political, and self-promotional framing of that awful day.
And I’m relieved he won’t be given a platform to do it again on Friday’s anniversary in lower Manhattan.
Because for Trump, everything is his for the taking, and absolutely nothing is sacred.
S.E. Cupp is the host of "S.E. Cupp Unfiltered" on CNN.