






Pearl, the author of “ ChatGPT, MD,” teaches at both the Stanford University School of Medicine and the Stanford Graduate School of Business. He is a former CEO of The Permanente Medical Group.
In the sweltering heat of 19th-century colonial Delhi, cobras were taking over the streets, creating a venomous problem. According to legend, British officials concocted a plan, offering a bounty for every dead snake brought to government offices. It worked. But not as officials had hoped.
Soon, locals began breeding and killing cobras for profit. And when the Brits ended the program, breeders released their now-worthless snakes back into the streets, turning a problem into a crisis.
This tale of unintended consequences, known as the “ cobra effect,” serves as a stark reminder that well-meaning policies can backfire when they fail to consider the relationship between human nature and economic incentives.
Medicare’s method of reimbursing doctors bears a striking resemblance to this parable. Originally established to control health care costs through calculated payments and budget caps, the payment model used by the Centers for Medicare and Medicaid Services has instead contributed to health care inflation and now threatens to compromise patient health.
Here’s how we got into this venomous situation — and what Congress should do to help.
The problem began with the Budget Reconciliation Act of 1989, a law that keeps physician payments relatively flat year after year, ensuring that total Medicare spending increases by no more than $20 million annually.
To appreciate the absurdity of this rule, it’s important to understand how Medicare calculates payments to doctors.
Each medical service — be it a doctor’s office visit, an X-ray or surgery — is assigned an intensity factor called a relative value unit, or RVU. Medicare then multiplies the number of RVUs by a fixed value per RVU to generate physician payments.
The problem arises when higher volumes of services cause annual CMS payments to exceed budget neutrality requirements. Medicare then lowers dollars per RVU, driving physicians to perform more procedures and see patients more often to preserve income. This, in turn, forces CMS to propose an even lower RVU value the following year, perpetuating a never-ending cycle of volume escalation and payment cuts.
Beyond the cycle of volume escalation and payment cuts, here are four more critical flaws in Medicare’s current payment model:
- Although budget neutrality aims to control overall Medicare costs, the law illogically targets physician income, which represents only 8 percent of all U.S. health care expenditures. A more logical strategy would seek to lower hospital costs ( 30 percent of total spending) or retail drugs (the fastest-rising source of spending).
- The requirement for budget neutrality is applied nationally, so it remains financially beneficial for individual doctors to increase the volume of services they provide in response to reductions in unit payments.
- The pandemic, exacerbated labor and medical supply costs, and Medicare cuts are straining primary care. This financial pressure is leading to physician burnout, prompting early retirements and contributing to a projected nationwide shortage of doctors. Those who continue practicing must handle increased patient volumes to offset declining payments. This necessity drives some to charge “ concierge fees,” inadvertently pushing low-income patients towards emergency rooms for routine care, escalating overall health care costs and delaying necessary treatments.
- The need to see more patients each day not only compounds physician burnout but also increases the risk of medical mistakes. In today’s rushed environment, with less time dedicated to each patient, 400,000 Americans die annually from misdiagnoses.
If Congress fails to act, today’s problems will spiral into a deeper health care crisis.
When government payments decline, the businesses funding private health care for 155 million Americans (half the country) are charged higher prices. Recent research concludes that higher employer premiums result in lower wages and significant job losses.
To safeguard the health of our nation and manage Medicare costs more effectively, Congress must take decisive action:
It’s time to move beyond the current fee-for-service model. Reimbursing clinicians based on the volume (not value) of medical services provided creates faulty incentives to do more (not to do better). We need a capitated model for physician payment: a single fee for the totality of care provided to a population of patients, one that incentivizes preventive medicine and chronic disease management. The Centers for Disease Control and Prevention estimates that effective control of chronic illness would result in 30 percent 50 percent fewer heart attacks, strokes and kidney failures.
Today, capitated models are paid to insurance companies. And because insurers aren’t involved in the provision of care, they have no means to control expenses other than imposing restrictive prior authorization requirements, which delay treatments and undermine patient outcomes. By contrast, prepaying doctors directly would spur much-needed innovation and improvements in medical practice. Innovative artificial intelligence tools and approaches, if used, would enhance the quality, accessibility and efficiency of American health care, helping doctors and patients prevent chronic diseases, avoid serious complications, and eliminate redundant or ineffective medical treatments.
To smooth the transition from the current fee-for-service model, CMS and Congress need to collaborate on a decisive five-year plan. The goal: Replace pay-for-volume payments with a capitation system that prioritizes value of care. Today, medical societies find themselves in contentious negotiations over who gets what portion of Medicare payments. Instead, CMS should encourage these societies to work together, forming multispecialty medical groups that are equipped to handle capitation. By offering transitional capital and support, Congress and CMS can help these groups implement solutions that keep patients healthier, thereby reducing the incidence of life-threatening heart attacks, strokes and cancers currently driving up Medicare spending.
Currently, the debate among CMS and health care groups focuses on whether the planned reduction in payments next year will be closer to 2.9 percent or 1 percent, and which specialties will face the harshest impacts. This myopic focus overlooks the larger issue: 98 percent of the reimbursement methodology remains unaddressed and ineffective.
If Congress authorizes these changes now, we can significantly enhance the physical and financial health of our nation, ensuring a sustainable health care system for future generations.













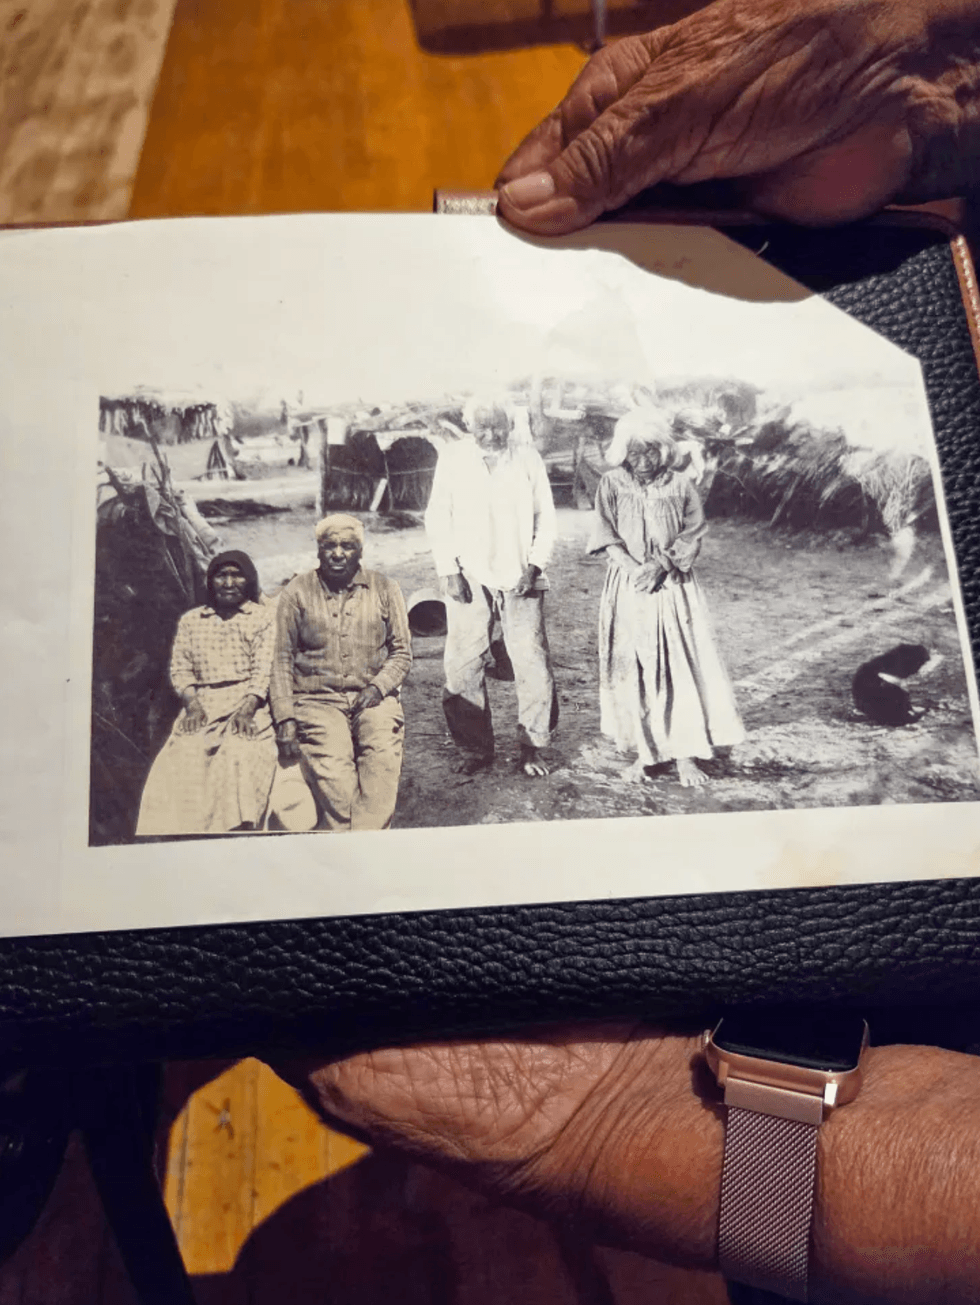 Lorraine Marquez Eiler’s photo of her great-great grandparents and her great-grandparents, who would walk about 50 miles through the Sonoran Desert to the springs.
 The Quitobaquito pond sits near the U.S.-Mexico border just west of the Lukeville port of entry on Monday, Aug. 24, 2026. The Trump administration is attempting to build a second border fence 150-feet from the existing border, which O’odham tribal members and environmentalists say would damage Quitobaquito, a sacred site to the O’odham and other indigenous people. Credit: Stephanie Casanova
 Construction equipment is seen near the U.S.-Mexico border just west of the Lukeville port of entry on Monday, Aug. 24, 2026. Credit: Stephanie Casanova
 Rep. Adelita Grijalva, left, and Tohono O’odham Chairman Verlon Jose listen as Lorraine Marquez Eiler, a Hia-C’ed O’odham elder, shares how her ancestors would hold ceremonies at Quitobaquito Springs. Grijalva visited the springs with tribal leaders on Monday, Aug. 24, 2026. Credit: Stephanie Casanova
 Sara Mae Williams, Justice of the Peace in Ajo and a Tohono O’odham citizen, shares their concerns regarding border wall construction on Tohono O’odham land at a town hall at the Ajo Plaza Rec Hall on Monday, Aug. 24, 2026. Credit: Stephanie Casanova