







Pearl, the author of “ ChatGPT, MD,” teaches at both the Stanford University School of Medicine and the Stanford Graduate School of Business. He is a former CEO of The Permanente Medical Group.
With a single ruling, the Federal Trade Commission removed the nation’s occupational handcuffs, freeing almost all U.S. workers from noncompete clauses that prevent them from taking positions with competitors for varying periods of time after leaving a job.
American medicine, especially, will benefit. The FTC projects the new rule will boost medical wages, foster greater competition, stimulate job creation and reduce health expenditures by $74 billion to $194 billion over the next decade. This comes at a crucial time for American health care, an industry where half of physicians report burnout and 100 million people (41 percent of U.S. adults) are saddled with medical bills they cannot afford.
The FTC’s final rule, issued in April, liberates not only new hires but also the 30 million Americans currently tethered to noncompete agreements. Scheduled to take effect in September — subject to legal challenges by the U.S. Chamber of Commerce and other business groups — the ruling will allow health care professionals to change jobs within the community rather than having to move 10, 20 or even 50 miles away to avoid breaching a noncompete clause.
Like all major rulings, this one creates clear winners and losers — outcomes that will reshape careers and potentially alter the very structure of U.S. health care.
Winners: Newly trained clinicians
Undoubtedly, the FTC’s ruling is a win for younger doctors and nurses, many of whom enter the medical job market in their late 20s and early 30s, carrying significant student-loan debt — nearly $200,000 for the average doctor.
Eager for a stable, well-paying position, young professionals join hospitals and health systems with the promise of future salary increases and more autonomy. But when these promises fail to materialize, noncompete clauses give clinicians little choice but to uproot their lives, move far away and start over. As one physician in rural Appalachia told the FTC, “Healthcare providers feel trapped in their current employment situation, leading to significant burnout that can shorten their career longevity.”
By banning noncompetes, the FTC’s rule will boost career mobility, spurring competition among health care employers to attract and, more importantly, retain top talent.
Currently, the rule comes with one notable asterisk: Nonprofit hospitals and health systems fall outside the FTC’s jurisdiction. However, the agency says these facilities might be at “a self-inflicted disadvantage in their ability to recruit workers.” Moreover, as Congress intensifies scrutiny on the nonprofit status of U.S. hospitals, those that reject the FTC’s guidelines may find themselves forced to comply through legislative actions.
Winners: Patients in competitive health care markets
The FTC’s ban on noncompete clauses will directly improve patient outcomes. For example, doctors and nurses who experience less burnout and greater job satisfaction are far less likely to make serious medical errors, studies show.
Further, clinicians who are now free to practice elsewhere in the community are likely to offer greater access, lower prices and more personalized service to attract and retain patients. Other doctors and nurses will join local outpatient centers, offering convenient and cost-effective alternatives to the high-priced diagnostic tests, surgeries and urgent care provided at nearby hospitals.
Losers: Large health systems
Made up of several hospitals in a geographic area, large health systems have traditionally relied on noncompete agreements to build market dominance. By preventing high-demand medical professionals such as radiologists and anesthesiologists from joining with competitors or starting independent practices, these health systems have managed to suppress competition while forcing insurers to pay more for services.
Currently, these systems demand high reimbursement rates from government and business payers. At the same time, they maintain relatively low wages for staff, creating a highly profitable model. Yale economist Zack Cooper’s research shows the consequence of the status quo: In highly concentrated hospital markets, prices go up and quality declines.
The FTC’s ruling will challenge those conditions, eroding health-system monopolies and shrinking their oversized bottom lines.
Losers: Hospital administrators
Individual hospitals have faced a unique challenge this past decade. Inpatient numbers continue falling nationwide, which makes it harder for hospital administrators to fill beds. This trend — driven by new technologies, evidence-based practices and changing insurance-reimbursement policies — have forced hospital administrators to adapt their financial strategies.
And adapt they did. Today, outpatient services account for half of all hospital revenue, reflecting aggressive acquisitions of local practices that offer physician consultations, procedures like radiological and cardiac diagnostics, chemotherapy, and same-day surgery.
Medicare and other insurers pay hospital-owned outpatient services more than local doctors and other facilities for identical services. By acquiring community outpatient practices, hospitals are paid higher rates without facing higher costs, thus generating large profits.
This strategy only works, however, if hospital administrators can prevent clinicians from quitting and returning to practice in the same community. If they do, their patients are likely to follow.
This is why the noncompete clauses are so essential to a hospital’s financial success. As expected, the American Hospital Association opposes the FTC’s rule, calling it “bad law, bad policy, and a clear sign of an agency run amok.”
Looking ahead
Today’s hospital systems are divided between haves and have-nots. Facilities in affluent areas enjoy higher reimbursements from private insurers, with greater financial success and higher administrator salaries (but not necessarily better patient outcomes). Rural hospitals grapple with low patient volumes while facilities in economically disadvantaged, high-population areas face greater financial difficulties.
None of these models are working for everyday Americans. The ultimate measure of health care policy should be its effect on patients. Based on the FTC ruling, the evidence is clear: Eliminating noncompete clauses will benefit patients greatly.













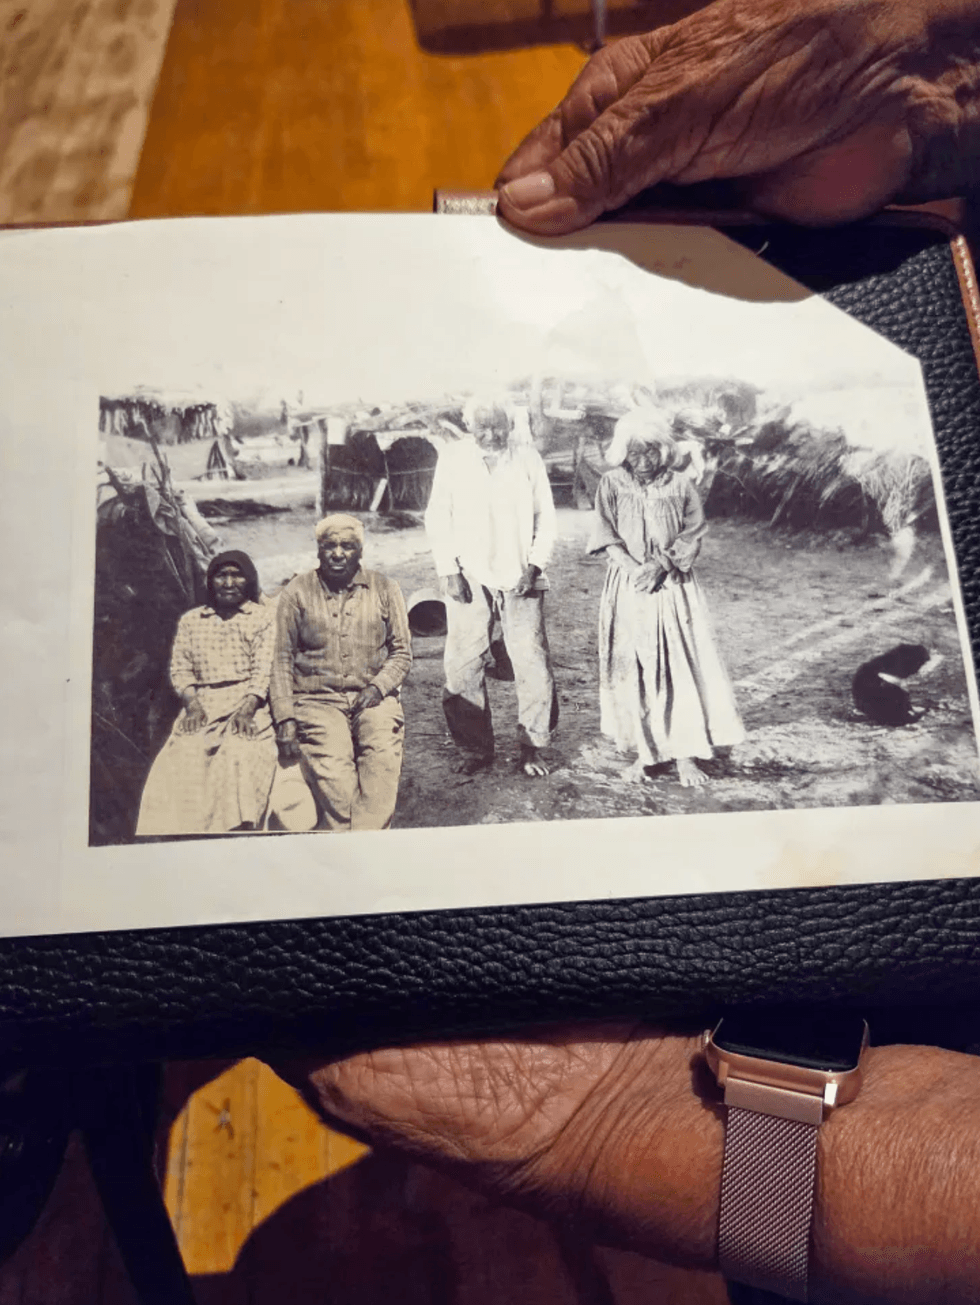 Lorraine Marquez Eiler’s photo of her great-great grandparents and her great-grandparents, who would walk about 50 miles through the Sonoran Desert to the springs.
 The Quitobaquito pond sits near the U.S.-Mexico border just west of the Lukeville port of entry on Monday, Aug. 24, 2026. The Trump administration is attempting to build a second border fence 150-feet from the existing border, which O’odham tribal members and environmentalists say would damage Quitobaquito, a sacred site to the O’odham and other indigenous people. Credit: Stephanie Casanova
 Construction equipment is seen near the U.S.-Mexico border just west of the Lukeville port of entry on Monday, Aug. 24, 2026. Credit: Stephanie Casanova
 Rep. Adelita Grijalva, left, and Tohono O’odham Chairman Verlon Jose listen as Lorraine Marquez Eiler, a Hia-C’ed O’odham elder, shares how her ancestors would hold ceremonies at Quitobaquito Springs. Grijalva visited the springs with tribal leaders on Monday, Aug. 24, 2026. Credit: Stephanie Casanova
 Sara Mae Williams, Justice of the Peace in Ajo and a Tohono O’odham citizen, shares their concerns regarding border wall construction on Tohono O’odham land at a town hall at the Ajo Plaza Rec Hall on Monday, Aug. 24, 2026. Credit: Stephanie Casanova